NIVIPIT phase 1b: intratumoural low-dose anti-CTLA4 with anti-PD1 gives 24.3% grade 3–4 treatment-related toxicity at 6 months
In 61 treatment-naive patients with metastatic melanoma, intratumoural ipilimumab at 0.3 mg/kg combined with intravenous nivolumab produced grade 3–4 treatment-related adverse events in 24.3% at 6 months, below the 30% threshold.
In the NIVIPIT phase 1b trial, 61 treatment-naive patients with metastatic melanoma were randomized 2:1, with 40 receiving intratumoural (IT) ipilimumab at 0.3 mg/kg plus intravenous nivolumab and 21 in the intravenous (IV) arm. Thirty-seven patients in the IT arm were evaluable for the primary endpoint, with grade 3–4 treatment-related adverse events in 24.3% at 6 months (57.1% in the IV arm), below the 30% threshold. ORR was 67% and CR 38% (ORR 52% and CR 14% in the IV arm). At a median follow-up of 55.5 months, median PFS in the IT arm was 13.8 months. Peak serum concentration of intratumoural ipilimumab was 2.2±1.7 µg/ml versus 42.2±12.3 µg/ml in the IV arm. The HoLISTIC framework shows that IT injection drives both local and distant immune responses.
Key data card
- Study type: Randomized, multicentre phase 1b clinical trial (NIVIPIT, NCT02857569)
- Sample size n: 61 treatment-naive patients with metastatic melanoma randomized 2:1: 40 in the IT arm and 21 in the IV arm; 37 in the IT arm evaluable for the primary endpoint
- Controls: Intravenous ipilimumab at 3 mg/kg plus nivolumab (the IV arm, used only as an internal control)
- Intervention/dose: Intravenous nivolumab at 1 mg/kg plus intratumoural ipilimumab at 0.3 mg/kg, every 3 weeks for 4 doses; then nivolumab at 3 mg/kg every 2 weeks for up to 12 months
- Follow-up: Median follow-up 55.5 months (IQR 48.2–62.8)
- Primary endpoint: Event-free survival from treatment-related grade 3–4 toxicity at 6 months (CTCAE v4.0)
- Primary endpoint result: 9 of 37 evaluable patients in the IT arm (24.3%) had a grade 3–4 treatment-related adverse event, below the 30% Fleming threshold; the abstract reports 22.6% (versus 57.1% in the IV arm)
- Statistics: Fleming two-stage design with α of 10% and 90% power (P0=50%, P1=70%); the two arms were not formally compared
- Safety: The injection procedure caused no grade ≥3 adverse events; only 1 grade 4 event occurred in the IT arm
- Evidence level: Full text
- Verification record: Europe PMC full-text XML (PMC13323097): Abstract, Results, Discussion, the statistics section of Methods and the legends for Figs. 1–5
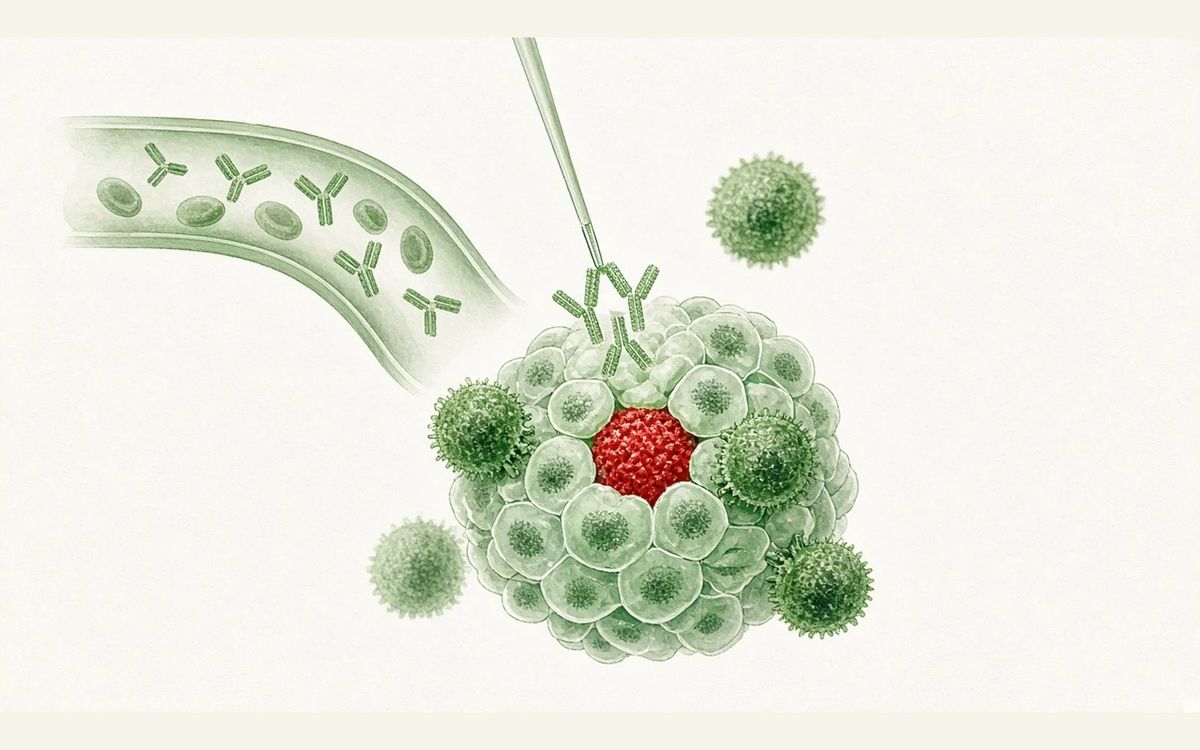
- Low-dose ipilimumab injected intratumourally
- Markedly lower systemic drug exposure
- Deeper responses in injected lesions
- Fewer activated Tregs in patients with DCB
Background and open questions
Intravenous combination of anti-CTLA4 and anti-PD1 can produce durable responses, but about 60% of patients experience grade ≥3 treatment-related adverse events, 1–4% of which are fatal in the real world, and only about half of eligible patients receive the combination in practice. Anti-PD1 is a non-depleting IgG4 whose efficacy plateaus once receptors are saturated (around 0.3 mg/kg); ipilimumab, by contrast, is an unmodified IgG1 that binds FcγR and mediates ADCC and phagocytosis, with both efficacy and toxicity rising with dose.
The NIVIPIT trial reported by Tselikas et al. in Nature tests a hypothesis: whether lowering the total ipilimumab dose tenfold to 0.3 mg/kg and injecting it directly into the tumour at 5 mg/ml can preserve the antitumour effect of high local exposure while reducing systemic toxicity, and whether fresh tumour biopsies can identify biomarkers of durable benefit.
Study design
This is a randomized, multicentre phase 1b trial that enrolled 61 treatment-naive patients with metastatic melanoma at 4 centres, randomized 2:1 to the intratumoural (IT) arm (40 patients) or the intravenous (IV) arm (21 patients), stratified by metastatic stage, BRAF status and PD-L1 expression. Both arms received intravenous nivolumab at 1 mg/kg, with the IT arm also receiving intratumoural ipilimumab at 0.3 mg/kg and the IV arm intravenous ipilimumab at 3 mg/kg, every 3 weeks for 4 doses, followed by nivolumab at 3 mg/kg every 2 weeks for up to 12 months.
The primary endpoint was event-free survival from treatment-related grade 3–4 toxicity at 6 months, using a Fleming two-stage design (α of 10%, 90% power) requiring 38 evaluable patients in the experimental arm. The IV arm served only as an internal control; the paper makes no formal comparison between arms and was not powered for efficacy comparison. A total of 162 intratumoural injections were given across 46 lesions, with fresh biopsies and blood samples collected at baseline and week 3.
Key results
The primary endpoint was met
Of the 40 patients in the IT arm, 37 were evaluable and 9 (24.3%) had a treatment-related grade 3–4 adverse event within 6 months, below the prespecified 30% Fleming threshold; 75.7% of the IT arm had no grade ≥3 toxicity versus 42.9% in the IV arm. The abstract reports 6-month grade 3–4 event rates of 22.6% versus 57.1%, which the authors describe as comparable to anti-PD1 monotherapy. The injection procedure itself caused no grade ≥3 adverse events.
Toxicity and pharmacokinetics over the full course
Cumulative treatment-related grade 3–4 adverse events over the whole follow-up were 32.5% in the IT arm and 66.6% in the IV arm, plateauing after 12 months; the IT arm had only 1 grade 4 event, while the IV arm had 52% grade 3 and 14% grade 4. Among 24 patients with serial samples, mean peak ipilimumab concentration was 2.2±1.7 μg/ml in the IT arm versus 42.2±12.3 μg/ml in the IV arm, with trough concentrations of 0.9±0.5 versus 8.4±10 μg/ml (P<0.0001).
Deeper responses in injected lesions
By RECIST v1.1, the best overall response rate in evaluable injected lesions in the IT arm was 65.7%, with 11 complete responses (31.4%) and 12 partial responses (34.3%) among 35 lesions; in the same patients, baseline non-injected target lesions had complete and partial response rates of 25% (10/40) and 20% (8/40), and the abstract reports 65.7% for injected and 50% for non-injected lesions. The best overall response rate in the IV arm was 62%.
No difference in survival
After a median follow-up of 55.5 months (IQR 48.2–62.8), neither PFS (log-rank P=0.2315) nor overall survival (P=0.1808) differed statistically between arms; median PFS was 13.8 months [4.4–27.7] in the IT arm and was not reached in the IV arm. Durable clinical benefit (DCB, response or stable disease sustained beyond 6 months) was associated with longer survival regardless of the route of anti-CTLA4 administration.
Activated Tregs fall only with DCB
Regardless of the route of ipilimumab administration, higher baseline activated Tregs and M2 macrophages predicted durable clinical benefit. At week 3, the proportion of CD4+CD25+CD39+ activated Tregs fell significantly only in patients with DCB, and the median ratio of CD8+CD39+ cells to those Tregs rose threefold, with no change in patients without DCB; baseline expression of FCGR1A, FCGR3A and FCGR3B was also higher in DCB tumours.
Mechanistic interpretation
Demonstrated in the paper: Both arms showed pharmacodynamic evidence of target engagement: membrane PD1 on tumour-infiltrating lymphocytes in injected lesions fell, while soluble PD1 rose in the tumour secretome and plasma; low-dose intratumoural ipilimumab likewise raised soluble CD25 and upregulated ICOS on circulating CD4+ and CD8+ T cells. Peripheral activation such as CD25 on CD8+ T cells and CD69 and OX40 on CD4+ T cells was seen mainly in the high-dose intravenous arm.
At the tumour level, DCB was associated with baseline MHC-I- and MHC-II-mediated adaptive immunity: higher CD8+PD1+ T cells, HLA-II protein, TH1 and TFH markers and B cell signatures, with no clear difference in tumour mutational burden between patients with and without DCB; intratumoural T cells, Tregs and CD68 expression were similar between the IT and IV arms. All of this is associative evidence.
Author hypotheses: The authors propose that, as in mice, Fc-intact IgG1 anti-CTLA4 can also deplete activated, tumour-specific Tregs in humans, but only in tumours that contain both activated Tregs and FcγR-positive effector cells. Peak concentrations in the IT arm were roughly 20-fold lower while the dose was tenfold lower, which the authors take to suggest partial retention of drug in the injected tumour and/or draining lymph nodes; the stronger peripheral activation in the IV arm may explain its higher toxicity.
Limitations and uncertainties
- Efficacy comparisons are limited by design: the trial was not powered for efficacy comparison, and the Discussion notes that the objective response rate of non-injected target lesions in the IT arm (50%) and overall survival were both lower than in the IV arm (response rate 65%); the authors attribute the IV arm's performance above historical benchmarks (50.6% to 58%) partly to the small arm size and residual imbalance after stratification.
- Samples are small and subgroup analyses smaller still: the IV arm had only 21 patients and the IT arm 37 evaluable for the primary endpoint; baseline flow cytometry Treg comparisons included only 13 patients with DCB and 7 without, and the between-group comparisons in Figs. 3 and 4 are two-sided Wilcoxon tests without multiple-comparison correction.
- Generalizability has boundaries: injected lesions were mostly lymph node and cutaneous or subcutaneous metastases, with few deep lesions; fresh biopsy markers require prospective validation in an independent cohort. The Results state a median overall survival of 50 months in the IT arm while the figure legend says it was not reached in either arm, an inconsistency in reporting.
Clinical and industry implications
If confirmed in later trials, intratumoural low-dose ipilimumab could offer a way to give dual checkpoint blockade that preserves activity in injected lesions while lowering systemic toxicity in settings where local control is critical, with the authors naming oligometastatic and neoadjuvant disease.
The results also suggest that efficacy depends mainly on pre-existing tumour immunity rather than the route of administration. Flow cytometry of CD4+CD25+CD39+ cells and secretome granzyme on fresh biopsies can be completed within hours; the authors argue this provides a basis for selecting and stratifying patients by tumour biology in future prospective trials, though prospective validation in an independent cohort is still needed.
Authors, source and verification
Evidence level: Full text; verification record: Europe PMC full-text XML (PMC13323097): Abstract, Results, Discussion, the statistics section of Methods and the legends for Figs. 1–5
Tselikas L, Susini S, Texier M, Yurchenko A, Routier E, Amini-Adle M, et al. Safety and efficacy of intratumoural anti-CTLA4 with intravenous anti-PD1. Nature. 2026 Apr 29. doi: https://doi.org/10.1038/s41586-026-10341-w
Primary field: Tumor immunology & cell therapy · Related: Intratumoural administration, Anti-CTLA4, Melanoma, Regulatory T cells, FcγR, Fresh biopsy biomarkers
Summary of a published paper or preprint, written from the original text; numbers are as reported by the authors. Not medical or investment advice. Corrections: contact@
Related science
In vivo BCMA CAR-T phase 1: 15 months of follow-up, one ongoing sCR
Green CAR-T cells attacking a red myeloma cell at right

Synthetic TCR library: on average only 56% of VDJdb TCRs reproduce their annotated reactivity
Green peptide-MHC complexes binding synthetic TCRs, with one non-reproducing case marked in red
Targeting ZMYND8 increases effector-like exhausted T cells in mice and enhances immunotherapy responses
Green immune cells attacking red tumour cells
One email, with links to every paper. Reports and custom landscapes: contact@inlightbio.com.