MDT-BRIDGE: neoadjuvant durvalumab plus chemotherapy, then surgery or chemoradiotherapy by team decision
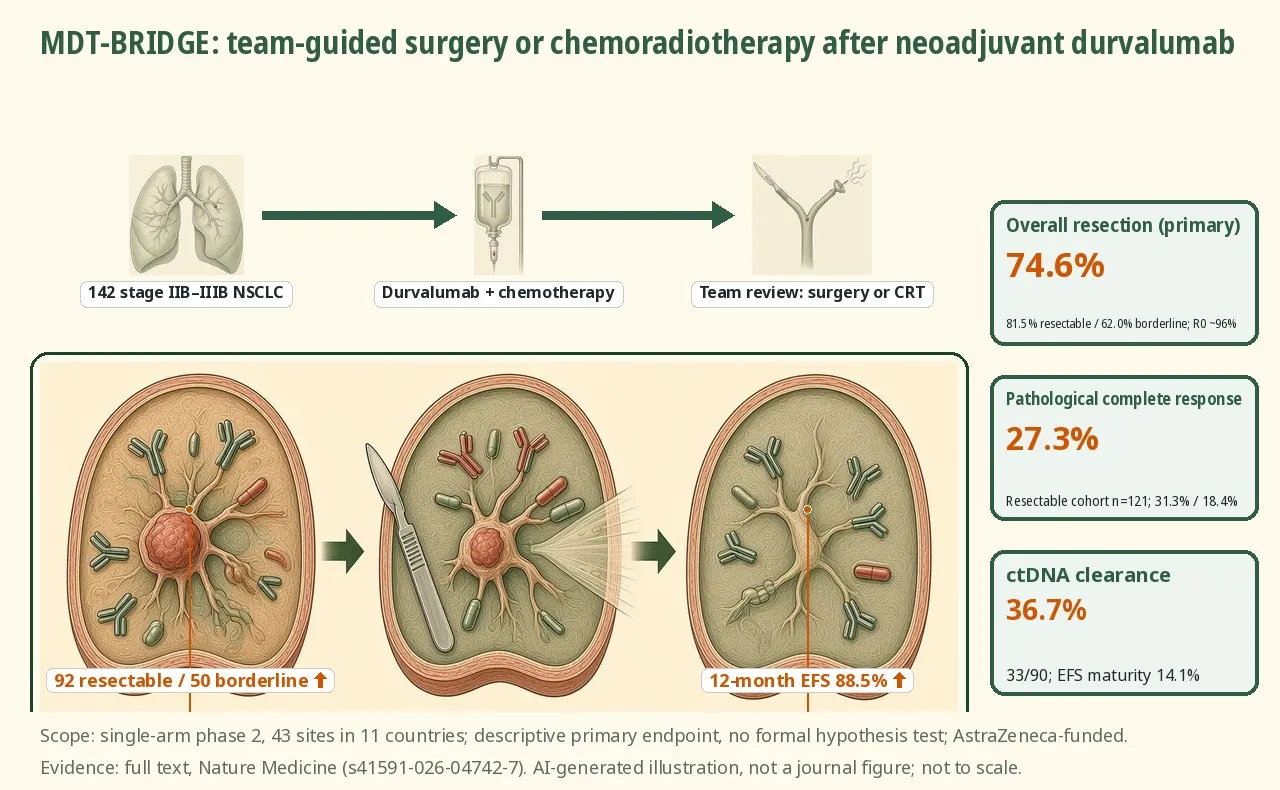
In the phase 2 MDT-BRIDGE trial, 142 patients with resectable or borderline resectable stage IIB–IIIB NSCLC received neoadjuvant durvalumab plus chemotherapy, then surgery or chemoradiotherapy as decided by a multidisciplinary team. The resection rate was 74.6%, pCR was 27.3% in the 121-patient resectable cohort, and 12-month EFS was 88.5%.
Background and open questions
Perioperative chemoimmunotherapy is standard for resectable NSCLC, but many stage III patients are borderline resectable and may instead receive chemoradiotherapy. The trial asked how patients fare when a multidisciplinary team chooses the local treatment after neoadjuvant chemoimmunotherapy.
Study design
Patients with stage IIB–IIIB disease received neoadjuvant durvalumab plus chemotherapy. A multidisciplinary team then assigned surgery or chemoradiotherapy, followed by adjuvant or consolidation durvalumab. ClinicalTrials.gov: NCT05925530.
Key results
- Overall resection rate was 74.6% (95% CI 66.7–81.6); 81.5% among patients resectable at baseline.
- pCR was 27.3% in the 121-patient resectable cohort (31.3% resectable at baseline vs 18.4% borderline).
- 12-month EFS was 88.5% (95% CI 81.5–92.9) at 14.1% maturity (20 of 142 events).
- Grade 3/4 treatment-related AEs in the neoadjuvant phase occurred in 25.9% and 17.9% of the resectable and unresectable cohorts.
Mechanistic interpretation
The results suggest neoadjuvant chemoimmunotherapy can be given before the final local-treatment decision, with team review then choosing surgery or chemoradiotherapy.
Limitations
- Single-arm design with no randomized comparator.
- EFS is immature (14.1% maturity); longer follow-up is needed.
- MDT decisions may vary between centres.
Authors and source
Reck M, et al. Nature Medicine (open access, CC BY-NC-ND 4.0). Received 9 September 2026, accepted 6 October 2026, published online 26 October 2026. https://doi.org/10.1038/s41591-026-04742-7. ClinicalTrials.gov: NCT05925530.
Numbers are as reported by the authors. Corrections: contact@
Related science
First-in-class METTL1 inhibitor STM9005 cuts tRNA m7G and slows AML and solid-tumor models
STM9005 blocks METTL1–WDR4, lowering tRNA m7G and translation of oncogenic mRNAs.

PHERGain 5-year data: PET-guided chemotherapy de-escalation in HER2-positive early breast cancer
PHERGain: PET-guided de-escalation with trastuzumab and pertuzumab.
A 256-model tumour organoid biobank, with 162 genome-wide CRISPR screens completed
Clustered tumour organoids, with red dots marking dependency genes hit in CRISPR screens
One email, with links to every paper. Reports and custom landscapes: contact@inlightbio.com.
Opens your email app with a pre-filled request; we add you by hand. Free, unsubscribe any time.